Is Robotic Surgery Safe?
What Nobody Tells You, From an Experienced Surgeon at the Controls
If you have been told you need surgery and the word “robotic” came up, there is a good chance you went home and started searching. Maybe late at night. Maybe you asked Google, or even ChatGPT. Some of what you found was accurate and some of it was not, and that mix can leave you more anxious than when you started.
Dr. Hesham Atwa has been part of more than 20,000 operations over his career, including more than 2,500 robotic procedures. He is chief of surgery at two hospitals, the author of Mastering Robotic Surgery, and has trained many other surgeons in robotics. He also believes that a well-informed patient is a calmer patient with a better recovery. Here are his honest answers to the questions he hears most.
First Things First: The Robot Does Not Operate On Its Own
This is the biggest misunderstanding out there. When researchers surveyed members of the public about robotic surgery, more than one in five believed the robot operates by itself or responds to spoken commands, almost like a self-driving car for surgery (Boys et al., Surgical Endoscopy, 2016). It is easy to see where that idea comes from. The word “robot” brings up a lot of science fiction.
The reality is much simpler. A surgical robot is a machine that the surgeon controls. It does nothing on its own and only moves when the surgeon moves it. The U.S. Food and Drug Administration puts it plainly: these systems cannot perform surgery without direct human control (U.S. Food and Drug Administration, Computer-Assisted Surgical Systems).
Fully independent surgical robots may arrive someday, perhaps ten or fifteen years from now, Dr. Hesham Atwa says, but that is not what is happening in operating rooms today. The surgeon is in complete control from start to finish.
What Actually Happens In the Operating Room
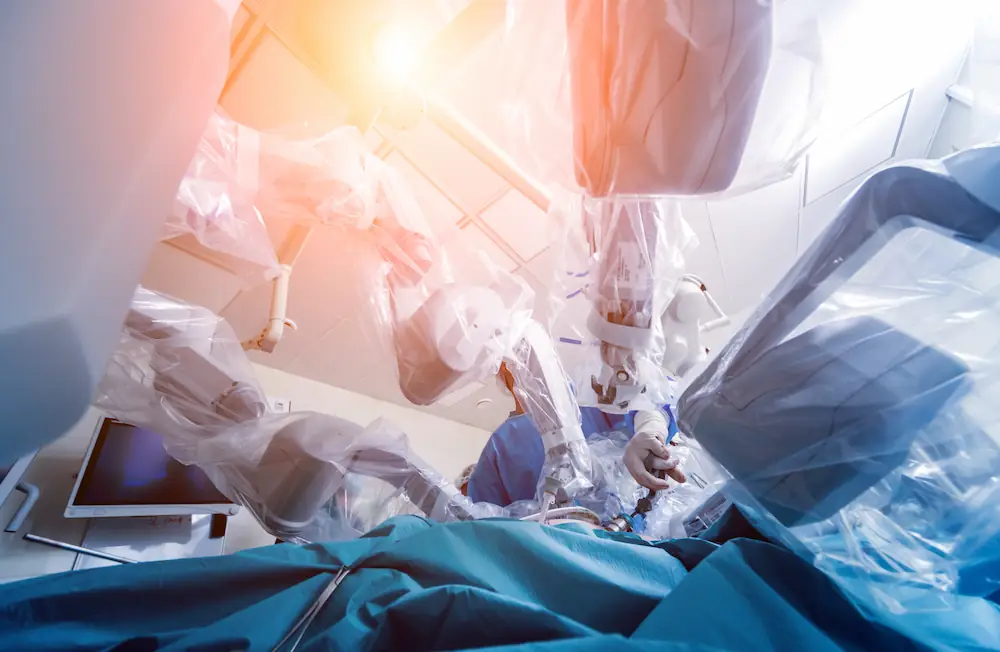
Here is the picture Dr. Hesham Atwa paints for his patients. While the patient is comfortably asleep on the operating table, he sits at a console just a few feet away. Looking into the viewer, he sees a magnified, three-dimensional view of the area being treated, with a sense of depth that no other approach provides. The robot’s arms are placed through a few small incisions, and his fingers control their every movement.
Dr. Hesham Atwa likes to compare the three ways of doing surgery to the history of the automobile. Open surgery is the horse and carriage. Laparoscopic surgery, the small-incision approach that changed everything about 25 to 30 years ago, is the Model T. Robotic surgery is like a Tesla. It places a computer between the surgeon and the patient, which adds precision and control, but the surgeon is still the one driving.
“What If the Machine Breaks?”
This is one of the most common fears patients bring up, and it is a fair question. The honest answer is that problems are extremely rare, and surgical teams are prepared for them.
Hospitals have backup generators that come on within seconds if the power goes out, and the robot itself has a battery, so it does not suddenly shut down in the middle of an operation. Out of the thousands of robotic procedures Dr. Hesham Atwa has performed, he can recall only once or twice when the system needed to be restarted, and it was back up and running within moments.
Occasionally an instrument has a mechanical issue, since the instruments work with small cables, but it is simply swapped out and the operation continues. These are minor interruptions, not emergencies.
Is Robotic Surgery Actually Safer?
In Dr. Hesham Atwa’s experience, yes, it is safer. But he is very clear about one thing, and it matters more than anything else in this article: the safety depends on the surgeon.
As Dr. Hesham Atwa puts it, “The robot doesn’t make a bad surgeon a good surgeon.” What it does is enhance the skill a surgeon already has, raising their game at whatever level they are.
With the robot, he can reach angles that are very difficult with standard laparoscopic instruments. He is seated comfortably, so there is far less physical and mental fatigue during a long operation. All of that helps cut down on complications and risk.
It helps to see how far surgery has come. With traditional open surgery, the incision is large. There is a higher risk of infection and of hernias forming at the incision, patients stay in the hospital longer, and full recovery often takes six to eight weeks. Laparoscopic surgery brought that down dramatically, with small incisions and patients feeling like themselves in about five to seven days. Robotic surgery builds on that by adding the precision of a computer-assisted system. Today, very few of Dr. Hesham Atwa’s operations need to be done the open way.
Who Should Not Have Robotic Surgery?
Here is something many surgeons online do not mention: robotic surgery is not right for everyone, every time.
During robotic and laparoscopic surgery, the abdomen is gently filled with carbon dioxide gas to create room to see and work. Most people tolerate this without any trouble. But a patient with a very weak heart or serious lung disease may not be able to handle that pressure. And if someone is critically ill, for example bleeding and unstable, the speed and direct access of open surgery may be needed. These situations are uncommon, in Dr. Hesham Atwa’s experience only about one or two percent of cases.
Even for patients with heart or lung problems, Dr. Hesham Atwa will usually try the minimally invasive approach first when it is safe to do so, because the benefits can be significant: a quicker recovery, less time in the ICU, and less pain afterward.
And patients are always allowed to say no. Dr. Hesham Atwa sees his job as explaining what he believes is best for each patient, the way he would explain it to his own family. If a patient prefers a different approach and he believes it would harm them or slow their recovery, he tells them so honestly and encourages a second opinion. In his words, “I’m not going to give you something that’s going to hurt you or give you a prolonged recovery.”
Questions To Ask At Your Consultation
A big part of choosing a surgeon comes down to a gut feeling. You meet someone and sense that this is a good person who will take care of you. That feeling matters. But Dr. Hesham Atwa points out that a good bedside manner is not enough on its own, and patients should feel comfortable asking about experience, too.
Ask your surgeon how many of these operations they have performed, and specifically how many robotically. Is this one of their first, or have they done hundreds? In Dr. Hesham Atwa’s opinion, you want someone who has done at least 50. The more procedures a surgeon has performed, the more experience they bring to yours.
It is also fair to ask whether you truly need surgery right now. A trustworthy surgeon will give a straight answer. Some patients come to see Dr. Hesham Atwa and he tells them, “You can live with this. It’s not bothering you, and I can’t make you any better.” Others do need surgery, and waiting could mean ending up in the emergency room with a more complicated situation. Some conditions can safely wait a few months, and some need attention right away. A good surgeon will say which group you fall into, even when the honest answer is that you do not need surgery at all.
What Recovery Really Feels Like
This is the part patients are most curious about, and where most are pleasantly surprised.
Most robotic procedures are done through three or four small incisions. A long-acting numbing medication is placed at those sites, which keeps patients comfortable for several hours after surgery. The incisions are closed with a waterproof skin glue, so patients can shower the next day.
Pain control has changed a lot over the years. Earlier in Dr. Hesham Atwa’s career, it was common to send every patient home with a large prescription of narcotic pain pills. Today he prescribes only a handful of mild pain pills, and most of his patients never even open the bottle. Tylenol and Motrin, as appropriate, taken on a regular schedule (about every six hours), usually do the job.
For the first day or two, patients feel sore, a lot like they did a hundred sit-ups. That soreness eases a little more each day. A heating pad over the incisions helps relax the muscles, and an abdominal binder supports the belly so coughing and sneezing are much more comfortable.
Dr. Hesham Atwa gives his patients a simple rule for increasing activity: if it hurts, stop. If you are sore the next day, you pushed a little too hard, so ease back. For the first two weeks, the focus is walking. After two weeks, patients can begin lifting light weights, around five or ten pounds, and keep building gradually as long as nothing hurts. For most procedures, patients feel like themselves again within about seven to ten days. Hernia repairs take a little longer to heal fully, about six to eight weeks, so the pace is a bit slower with those.
Getting Back to Work
Many of Dr. Hesham Atwa’s patients are doctors, nurses, and business owners who cannot afford to be away from work for long. Some have returned to work within two or three days. Others, especially those with physically demanding jobs that involve heavy lifting, need a bit more time before going back to full duty.
If an employer allows light duty, that can be a good way to return sooner while finishing the healing process. Dr. Hesham Atwa talks through each patient’s job with them and helps plan their return.
The Honest Bottom Line
The robot never operates on its own. It is a remarkable tool that gives the surgeon better vision, better precision, and better control, and for most patients that means less pain and a faster recovery. But the real safety feature is the experience of the surgeon sitting at the console.
Ask questions. Expect honest answers. And remember that you are always allowed to say no. If you have been searching late at night for answers about robotic surgery, Dr. Hesham Atwa and his team would be glad to answer your questions in person.
Ready to talk it over? Contact our office to schedule a consultation with Dr. Hesham Atwa and the team at Long Island Laparoscopic Doctors.
References:
U.S. Food and Drug Administration. Computer-Assisted Surgical Systems. Updated September 2026. https://www.fda.gov/medical-devices/surgery-devices/computer-assisted-surgical-systems
Boys JA, Alicuben ET, DeMeester MJ, et al. Public perceptions on robotic surgery, hospitals with robots, and surgeons that use them. Surgical Endoscopy. 2016;30(4):1310-1316.

Have questions about your treatment options?
Schedule a consultation with our team.
Book a Consultation